
Managing pain and stroke risk while staying active is a juggling act
I've faced delayed MRIs, pain medication, and an ambulance ride to the hospital
Written by |





I have previously written about mitigating stroke risk while having lower back and spine problems that inhibit my exercise plan. I must exercise to stay as healthy as possible with Fabry disease (FD).
After receiving another steroid injection in my left sacroiliac joint on Aug. 19, and another spine epidural steroid injection on Oct. 15 for ongoing lower back and sciatic nerve pain, I still ended up in an orthopedic urgent care clinic for severe pain on Oct. 22. The pain was excruciating, and the injections weren’t working to reduce it.
The urgent care clinic ordered an MRI of my lumbar spine, but they couldn’t perform the scan at their facility because the electrophysiology team at Duke Health needed to place my pacemaker in MRI mode before the scan. So I couldn’t get the MRI done until Nov. 12, despite my ongoing severe pain. The urgent care clinic did prescribe a pain medication, but I try to avoid pain medications because I’m reluctant to take opioids. Also, these medications have caused me brain fog in the past, and I need a clear mind for work and regular life.
However, I needed relief, so I agreed to take a new non-opioid, short-term pain medication, which significantly reduced my pain and didn’t cause brain fog. I took it for 13 days and experienced the least back pain I’ve had in years.

Before I took the new medication, I did what I always do and added it to my saved list of medications in the drug interactions tool I use to avoid unsafe interactions. The report didn’t list any major interactions, but there were several moderate ones. Moderate interactions typically mean I must space the interacting medications at least a couple of hours apart.
Next, I gave my medication schedule to a Duke University Medical Center (DUMC) pharmacist for approval. Due to my heart transplant in 2020, moderately high blood pressure, and other needs, I take one or more medications every two hours for most of the day. I set seven alarms on my phone each morning to stay on schedule. I also take Tylenol frequently to take the edge off my overall body achiness from FD. I add an alarm to record when I take Tylenol.
The fun really starts
Unfortunately, according to U.S. Food and Drug Administration instructions, the new pain medication shouldn’t be taken for more than 14 consecutive days. On my 13th day, before I took the evening dose, I became extremely dizzy. But it wasn’t the vertigo that sometimes occurs with FD. The dizziness was so severe that I was unable to walk and became extremely nauseous. It was quite scary!
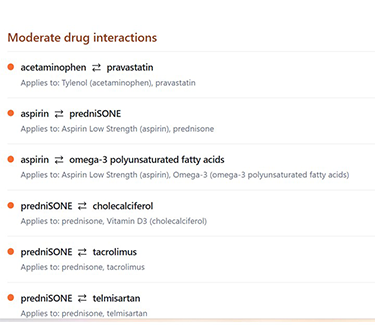
A screenshot of Jerry Walter’s possible medication interactions. (Courtesy of Jerry Walter)
My wife, Angela, and I thought it might be a stroke, which is somewhat common with FD, so she called 911. Fire department first responders arrived ahead of the ambulance for immediate care. Then the ambulance with EMTs arrived and transported me to the DUMC emergency department (ED).
I had a difficult time describing the dizziness until one of the ED neurologists asked if it was like being on a boat. That is the best description of what I felt. I had no balance. Standing and walking were impossible.
The neurology team performed all the standard tests, with instructions such as “follow my finger with your eyes,” “touch my finger, then touch your nose,” “slide your heel up your shin,” etc.
Fortunately, a brain MRI and CT scan revealed no signs of a stroke. A transient ischemic attack (TIA) is unlikely because, after the debilitating dizziness, less severe dizziness continued, unlike the short-term nature of a TIA.
I’m now seeing an occupational therapist to treat a possible vestibular disorder as the cause of my dizziness. I suspect the new pain medication may have played a role, but that is speculation, not fact.
Despite the National Fabry Disease Foundation’s frequent reminders about the B.E. F.A.S.T model for reacting to possible strokes, I didn’t act fast enough for the emergency room’s neurology team to use a blood clot-busting medication if the problem was a clot. When the dizziness started, I took a nap, hoping it would be gone when I woke up, and I missed the treatment window. I didn’t automatically think of a possible stroke when I should have. Luckily, it wasn’t a stroke, but it is a reminder of the importance of acting quickly and recognizing the B.E. F.A.S. T. warning signs of a stroke.
After all the temporary excitement, I went back to the DUMC for an updated MRI, which showed many progressing spine problems. The new scan should help my physiatrist and orthopedic specialist to determine next steps to reduce the pain to enable me to stay active. Being active is so important to staying healthy with FD.
Note: Fabry Disease News is strictly a news and information website about the disease. It does not provide medical advice, diagnosis, or treatment. This content is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Never disregard professional medical advice or delay in seeking it because of something you have read on this website. The opinions expressed in this column are not those of Fabry Disease News or its parent company, Bionews, and are intended to spark discussion about issues pertaining to Fabry disease.


Leave a comment
Fill in the required fields to post. Your email address will not be published.